
I don't know anything (not very smart). May or may not have positions in stocks I mention. Likes are bookmarks only.
Miami
Joined February 2021
- Tweets980
- Following370
- Followers812
- Likes2.6K

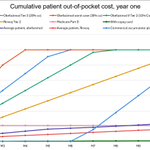
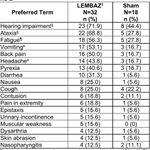






Can't believe I'm about to defend this name. Respectfully, I think that slide is being misread. Assume mgmt sticks to its >$80K net price, gets covered on most plans, and payers punish the price with a non-preferred tier at 20–30% coinsurance.
Commercial out-of-pocket is capped (ACA max ~$12K in 2027) and copay cards cover most of it, so the tier mostly changes when patients pay, not what they pay. The real drop-off is Medicare (no copay cards) and accumulator plans once a ~$14K card max runs out.
On profile (slightly weaker induction than Rinvoq, stronger maintenance, cleaner safety, no TNF-failure label restriction), my base case is Rinvoq-like usage or better, and Rinvoq is ~10–15% of US UC advanced-therapy patients today. There’s also a TON of switching in IBD. If you believe the obe maintenance data, patients stay on longer, so its share of patients on therapy should run above its share of new starts.
At $80K net (After rebates + discounts +copay support etc), a 9–13% share of a ~400K patient pool by 2037 is ~$2.5–3.5B in US UC alone.
The alternative, pricing near Rinvoq to win Tier 2, doesn’t pay: even at 1.2x Rinvoq’s net, revenue per patient falls >50%, so they’d need ~2.2x the patients just to break even. Pricing high and launching 2L+ is the right call until volume offsets.


$abvx this slide makes sell side forecast ridiculous and buyout hope at current valuation diminished. Plus CD is not in most buy side models anyway as their legal teams only allow a short US LOE. Very comfortable with two stage capitulations: $60-70 then $30 post launch


Can you short enough NUVB?
51:45 onwards
nitter.gq/i/spaces/1QnYBYjWVVOBn…
1
157


What's the bear case on $SVRA? Manufacturing?
It's rare that you have the underlying data and can run your own actual tipping point analyses on endpoints.
Robust Primary ✔️
Multiple Secondaries Trending / Nominally Sig. ✔️
IMPALA 1 and 2 showing the same thing ✔️
Not perfect but 2 trials in a rare disease with clear mechanism.

3
7
1,828

Lots of people on X call themselves dumpster divers. None of them are competition for me.
Small position in $KYNB. The biggest overhang (other than the pipeline) was the NovaQuest balloon payment, and they've paid it down.
Q4: hopefully they dump roxadustat on a partner for any amount upfront. Worst case, they get some funds (you know the usuals) to finance it and get a cash infusion. FG-3246 is a potentially interesting post-PSMA radiotherapy.
I am also short a small amount of $ARQT which is risky given recent run. But royalty pharma paid $100M to AZ for a 3% royalty on Zoryve and guided to a HSD/LDD IRR. On consensus that’s 20%+, even if the royalty ends in 2032 (10 years from First commercial sale). 20% wouldn’t clear a competitive auction. Read: RP sees sales well below the Street, or the IP is shakier than it looks.
3
4
1,120
Need to be above consensus for current valuation to make sense and I think they will burn a bunch of cash prosecuting label expansion + ARQ-234 is probably uncompetitive?
1
1
517

$LRMR y'all are crazy how you're valuing this company. FDA START program, filed BLA, and patients are lining up to be in the phase 3 (go look at the chats) regardless of what you think of anaphylaxis risk.


3
12
1,750
$KTTA This is sort of home run efficacy data with best-in-class safety profile. Literally double to triple the response of other trials, 1/3 the rash and 1/5th the diarrhea and no LVEF reductions, no retinopathy, and no D/C due to AEs.

$ktta was waiting for the basket trial to readout as an overhang. I think NF1 will look good 2H.