

Interventional Neurologist & Neuro-critical care specialist, Autodidact, Iconoclast, Agentic enthusiast, Technophile, Sempiternal scholar & Teacher
DM, FRCP, FICCN, EDSI, EDNI
Joined July 2009
- Tweets6.3K
- Following342
- Followers33.9K
- Likes10.9K







XRP Ledger Announces retweeted
Came in with complaints of feeling of weakness of left index tip. Flummoxed me a bit till the full exam
There is a peculiar pleasure in diagnosing a condition out of your specialty: something that you studied a long time ago in your undergrad.
Kind of makes up for all the unnecessary and useless stuff that you had to study back then: a partial vindication
Don’t you think?
Unsteady gait and some tripping
Lady with long standing rheumatoid arthritis and prior mono neuritis multiplex
On examination- mild sensory deficits in the soles


Ncv shows absent SNAPs in the right foot ( med and lat plantar)
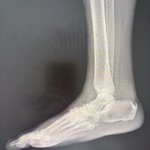
Exam shows a unilateral rocker bottom foot


Satralizumab Phase 3 METEOROID Trial is the First-Ever Positive Trial in MOGAD
(AAN 2026 / Life Science Daily News / NeurologyLive 2026)
Impact: STZ ↘️68% relapse risk reduction, 79% reduction in active MRI lesions, 73% reduction in rescue therapy need.
MOGAD previously had NO approved therapies and this is good news as pts relapse on existing therapies
XRP Ledger Announces retweeted
🚨 Burning Vertex Syndrome: A novel headache 🔥
A common problem in the Neurological OPD, well described by our colleague Pravin Thomas et al
🧠 Curr Opin Neurol 2025
➡️ Episodic, burning pain localized to the vertex (10–20 cm zone)
➡️ Mostly affects women (~65%), avg. age ~41
➡️ Duration: 1 min to 24 hrs, often <4 hrs
➡️ Frequency: daily to 1–3x/week
⚠️ Associated features in 76%:
•Nausea, vomiting
•Photophobia/phonophobia
•Autonomic signs
•Localized warmth (rare)
🧬Hypothesized mechanism? Small fiber scalp neuropathy
💉 Interesting finding: GON block helped in 2 patients
#NeuroTwitter #Headache


XRP Ledger Announces retweeted

They’re not even conducting Exams fairly & They want us to believe that they’re conducting Elections fairly.
A 36 year old obese man on Rx for schizophrenia, diabetes and metabolic syndrome, comes to you with a six month hx of neck pain. On examination there are no focal neurological deficits. Neck movement is slightly restricted
This is his Xray

XRP Ledger Announces retweeted

If you see a team walking around the hospital, kindly refer to them by the appropriate name:
⚕️A ganglia of neurologists
⚕️An inflammation of rheumatologists
⚕️A caffeine of nurses
⚕️A murmur of cardiologists
⚕️A croup of pediatricians
⚕️ Infectious disease docs in clusters
Just went through a neuropsychological assesment of a child who was referred for difficulty with studies and behavioural phone addiction .
The psychologist spent 10 minutes talking with him and sent me a report that he seemed like a bright child and did not seem to have ADHD.
Contrast this with an assesment performed for his sibling in the US who underwent a detailed assesment and was finally diagnosed with mild ADHD. After starting medications, the child improved significantly.
These were the tests the second child underwent
1. a clinical Interview
2.Behavioral Observations
3. Wechsler Intelligence Scale for Children - Fifth Edition (WISC-V)
4.The Beery-Buktenica Developmental Test of Visual-Motor Integration - Sixth Edition
5.Delis-Kaplan Executive Function System (D-KEFS)
6.Conners' Continuous Auditory Test of Attention
7.Conners' Continuous Performance Test - Third Edition
8.Behavior Assessment System for Children - Third Edition, Parent, Teacher and Self report forms
9.Behavior Rating Inventory of Executive Function - Second Edition, Parent and Self report forms
The difference in quality of the tests was astounding and eye-opening. I was unable to even face the parent with such a shoddy test report.
We need to do better than just make diagnoses based on a hunch.
It's a big problem in India, where we often take shortcuts; maybe due to lack of time or large OPDs....but we compromise tremendously on quality and hardly ever make any edge contributions
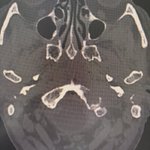
A 75 year old 🧔with gradually increasing left sided headache of 1 month duration
No fever/ ear discharge
No hx of Diabetes
O/e: temporal skull tenderness
Clinical dd/‘s : Skull base osteomyelitis/ metastasis
MRI/CT ; show an ill defined soft tissue in the region of the left occipital console and left lateral aspect of the Atlantic occipital joint
What are your thoughts on?


Occipital condyle lesions are overwhelmingly metastatic in origin (>90%) from prostate, lung , breast : the rest are due to primary skull base tumors or rarely due to infections such as Tb
Waiting for a PET-CT😃


Through 25 years of medicine, i followed a very conventional path as did all my peers. Study a theoretical topic intensely for a few months to years, then take baby steps towards practical applications. In the case of Neurointervention, it literally took years and learning from numerous mentors and proctors, before i developed a semblance of confidence in most procedures.
Coding was an esoteric and complex task that seemed out of bounds and in the realm of dedicated software developers. This made translation of my medical ideas into practical applications, almost impossible without a great deal of coordination with a developer. In the last 6-8 months, the roll out of multiple LLMs and agents has finally bridged that gap. 80-90% of the work is now planned and executed by me. The last 10-20% (app store launches/ backend work) still requires a developer right now, but it's fantastic to see my work coming to fruition.


Sensory deficits in spinal cord lesions; because of the peculiar arrangement of spinothalamic tracts inside the cord such that the sacral fibres lie outermost: Intra and extra medullary lesions produce contrasting sensory deficit patterns
Intramedullary is like a bat ‘inside’ the house: it is suspended and does not touch the bottom ( sacral sparing)
Extra medullary is like a ‘cat’ outside the house which is trying to climb up

The ESOC 2026 just concluded (May 6–8, Maastricht) with major stroke trial results : 3 positive outcomes and 2 negatives
🚀ATTRACTION (tirofiban post-EVT positive),
🚀ATILA (tirofiban in tandem lesions positive),
🚀GALLOP-2 (semaglutide neuroprotection positive),
↘️TECNO (IA tenecteplase negative), ↘️GREEN (glenzocimab futility)