

T, B, & NK cells and Stem cell scientist for 50 yrs , Commercialized CD4/IL-2r, CD34 Mabs at BDMC &ABI TaqMan mRNA Gene Expression during human genome project.
California
Joined September 2010
- Tweets26.8K
- Following946
- Followers1.2K
- Likes46.3K


Pinned Tweet
Andy Blidy
Caravello A and Blidy A (2026) A
proposed convergent molecular
chain linking senescence, cancer,
and chronic infection to a correctable
failure of dendritic cell instruction.
Front. Immunol. 17:1861044.
doi: 10.3389/fimmu.2026.1861044
COPYRIGHT
© 2026
HYPOTHESIS AND THEORY article
Front. Immunol., 30 July 2026
Sec. Dendritic Cells, Macrophages and APC Immunology
Volume 17 - 2026 | doi.org/10.3389/fimmu.2026.1…
A proposed convergent molecular chain linking senescence, cancer, and chronic infection to a correctable failure of dendritic cell instruction
Andrew Caravello and Andrew Blidy
The document proposes a paradigm shift in immunology, focusing on correcting immune instruction via dendritic cells to treat aging, cancer, and autoimmunity.
Main Concept
•The immune system functions like a school, with dendritic cells as teachers directing immune responses.
•Aging and disease impair dendritic cell polarity, leading to tolerance, cancer hiding, or autoimmunity.
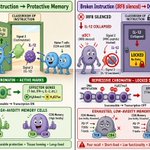
•The core failure involves the silencing of IRF8, reducing IL-12 and impairing immune education.
•Restoring dendritic cell function can re-establish proper immune discrimination.
Proposed Intervention
•Use patient-derived monocytes matured into alpha-type-1 polarized dendritic cells (αDC1).
•Infuse these cells to deliver IL-12, reactivate IRF8, and restore immune surveillance.
•This approach acts as a biological reboot, clearing senescent cells and correcting immune default states.
•The method can be tailored for tolerance or immunity, depending on clinical goals.
Implications and Industry Movement
•Current treatments target downstream effects; this approach addresses upstream instruction failure.
•Major pharma invests in scalable cell manufacturing, positioning dendritic cell therapies at leverage points.
•The shift suggests a focus on rewriting immune "manuals" rather than symptom suppression.
To answer the question about the role of dendritic cells in aging, I have drawn directly from the provided document, which presents a novel immunological framework. This framework positions dendritic cells as central 'teachers' in the immune system, whose dysfunction is a key driver of aging and age-related diseases. Below, I explain the mechanisms, consequences, and potential interventions, using examples and clear analogies from the document. Dendritic Cells: The Immune System's Teachers Dendritic cells (DCs) act as the primary instructors of the immune system. They determine whether other immune cells (like T cells) should attack a threat or tolerate it. When dendritic cells provide clear and accurate instructions, the immune system efficiently clears damaged or senescent cells, prevents early cancers, and keeps inflammation under control.
What Goes Wrong with Aging? As we age, or under chronic stress (such as cancer or persistent infection), the following sequence occurs: Senescent cells (sometimes called 'zombie' cells) accumulate especially in bone marrow and release inflammatory signals known as the senescence-associated secretory phenotype (SASP).These signals keep a protein called STAT3 switched on in the bone marrow, where new immune cells are made.STAT3 then recruits enzymes that silence a master gene called IRF8, which is essential for the most important type of dendritic cell (cDC1).Once IRF8 is silenced, dendritic cells stop producing the key messenger IL-12 and lose their ability to properly instruct the immune system.
Consequences Immune surveillance collapses: The body stops efficiently clearing senescent cells and early tumors. Imbalance between attack and tolerance: The immune system may tolerate threats it should attack, or attack the body's own tissues (autoimmunity).Chronic inflammation and disease: More than twenty disease settings are linked to this failure of dendritic cell instruction. Example Analogy The document compares the immune system to a school, with dendritic cells as teachers. If the teachers (dendritic cells) give the wrong lessons or fall silent, the students (other immune cells) become confused, leading to poor performance (disease, aging, cancer).
I have drawn directly from the provided document, which presents a novel immunological framework. This framework positions dendritic cells as central 'teachers' in the immune system, whose dysfunction is a key driver of aging and age-related diseases. Below, I explain the mechanisms, consequences, and potential interventions, using examples and clear analogies from the document.
Dendritic Cells: The Immune System's Teachers
Dendritic cells (DCs) act as the primary instructors of the immune system. They determine whether other immune cells (like T cells) should attack a threat or tolerate it. When dendritic cells provide clear and accurate instructions, the immune system efficiently clears damaged or senescent cells, prevents early cancers, and keeps inflammation under control.
What Goes Wrong with Aging?
As we age, or under chronic stress (such as cancer or persistent infection), the following sequence occurs:
•Senescent cells (sometimes called 'zombie' cells) accumulate and release inflammatory signals known as the senescence-associated secretory phenotype (SASP).
•These signals keep a protein called STAT3 switched on in the bone marrow, where new immune cells are made.
•STAT3 then recruits enzymes that silence a master gene called IRF8, which is essential for the most important type of dendritic cell (cDC1).
•Once IRF8 is silenced, dendritic cells stop producing the key messenger IL-12 and lose their ability to properly instruct the immune system.
Consequences
•Immune surveillance collapses: The body stops efficiently clearing senescent cells and early tumors.
•Imbalance between attack and tolerance: The immune system may tolerate threats it should attack, or attack the body's own tissues (autoimmunity).
•Chronic inflammation and disease: More than twenty disease settings are linked to this failure of dendritic cell instruction.
Example Analogy
The document compares the immune system to a school, with dendritic cells as teachers. If the teachers (dendritic cells) give the wrong lessons or fall silent, the students (other immune cells) become confused, leading to poor performance (disease, aging, cancer).
Why Is This Important?
This is not just another story about inflammation and aging. The document argues that the failure of dendritic cell instruction is a specific, upstream, and potentially correctable problem. Instead of treating the symptoms (like inflammation or cancer), the focus should be on restoring the dendritic cells' ability to instruct the immune system correctly.
Potential Intervention: The Biological Reboot
The proposed solution is to manufacture new, properly instructed dendritic cells outside the body and infuse them back into the patient. These cells can restore the immune system's ability to clear senescent cells and rebalance the immune response, potentially slowing or reversing aspects of aging.
Example Implementation:
•Take a patient's own monocytes (a type of white blood cell).
•Mature them outside the body into alpha-type-1 polarized dendritic cells (αDC1) using specific signals.
•Infuse these cells back into the patient, where they restore proper immune instruction.
Summary Table: Dendritic Cell Role in Aging
StepMechanismConsequence
1Senescent cells release SASPto Chronic inflammation
2STAT3 activation in bone marrowto Silencing of IRF8 gene
3Loss of IL-12 production by DCsto Poor immune instruction
4Immune surveillance failsto Aging, cancer, autoimmunity
In summary: Dendritic cells are central to immune system function and aging. Their dysfunction, driven by molecular changes as we age, leads to a breakdown in immune surveillance and contributes to age-related diseases. Restoring their function may offer a powerful new approach to healthy aging.
Analyze how dendritic cell modulation could reshape treatment paradigms for aging-related diseases.
To analyze how dendritic cell (DC) modulation could reshape treatment paradigms for aging-related diseases, I have synthesized evidence and arguments from the provided document. The document presents a paradigm shift: instead of targeting downstream symptoms (like inflammation or cancer cells), it proposes restoring the central instructional role of dendritic cells to correct immune dysfunction at its source. Below, I break down the current state, the proposed shift, and the practical implications for treatment.
Current State: Treating Symptoms, Not the Source
•Traditional Approaches: Most current therapies for aging-related diseases (cancer, autoimmunity, chronic inflammation) focus on downstream effects—killing cancer cells, blocking immune checkpoints, suppressing inflammation, or clearing senescent cells with drugs.
•Limitations: These approaches often deliver incomplete or temporary benefits because they do not address the root cause: the loss of proper immune instruction due to dendritic cell dysfunction.
The Paradigm Shift: Dendritic Cell Modulation
•Central Hypothesis: Dendritic cells are the 'teachers' of the immune system. When their instructional capacity is lost (due to molecular changes like STAT3 activation and IRF8 silencing), the immune system defaults to tolerance, allowing aging, cancer, and autoimmunity to progress.
•Modulation Strategy: The proposed intervention is to manufacture new, properly instructed dendritic cells (specifically, alpha-type-1 polarized dendritic cells or αDC1) outside the body and infuse them back into the patient. These cells restore the immune system's ability to clear senescent cells and rebalance attack/tolerance.
Example Implementation:
•Take a patient's monocytes or use donor cells.
•Mature them into αDC1 using interferon-gamma and multi-TLR signals outside the body (away from the STAT3/IRF8 silencing environment).
•Infuse these cells back into the patient, where they deliver a strong IL-12 pulse, restore IRF8 expression, and reboot immune surveillance.
How This Reshapes Treatment Paradigms
1.Upstream Correction vs. Downstream Management:
oInstead of treating each symptom or disease manifestation separately, DC modulation targets the upstream instructional failure, potentially correcting multiple downstream problems at once.
2.Personalized and Adaptive:
oThe same cell manufacturing process can be tuned for different outcomes: boosting immunity (for aging, cancer) or inducing tolerance (for autoimmunity, transplantation).
3.Reduced Need for Chronic Suppression:
oBy restoring proper immune instruction, there may be less reliance on chronic immunosuppression or repeated drug interventions.
4.Potential for Disease Modification:
oRather than just managing symptoms, this approach could modify the course of aging-related diseases by reactivating the body's own surveillance and repair mechanisms.
Industry Implications and Opportunities
•Scalable Manufacturing: Major pharmaceutical companies are investing in cell therapy manufacturing platforms, recognizing the leverage of producing instructional cells at scale.
•Broad Applicability: This approach could impact not only aging and cancer, but also autoimmunity and chronic post-infectious syndromes that share the same upstream polarity failure.
Summary Table: Comparison of Paradigms
Traditional ParadigmDendritic Cell Modulation Paradigm Treats symptoms (inflammation, cancer, etc.)Targets root cause (immune instruction failure)
Multiple drugs for multiple diseases.....Single cell-based intervention for multiple conditions
Chronic management.....Potential for disease modification ....Focus on effectors/checkpointsFocus on restoring immune 'teachers'
In summary: Dendritic cell modulation represents a shift from symptom management to root-cause correction in aging-related diseases. By restoring the immune system's instructional capacity, this approach could enable more effective, durable, and broadly applicable treatments, fundamentally changing how we approach aging, cancer, and autoimmunity.

Andy Blidy retweeted

$NWBO $MRNA $MRK
#ESMO26 #DCVax #DCVaxForBraelyn #GBM #CancerImmunotherapy
𝗠𝗼𝗱𝗲𝗿𝗻𝗮’𝘀 𝗻𝗲𝘄 𝗺𝗥𝗡𝗔 𝗰𝗮𝗻𝗰𝗲𝗿-𝘃𝗮𝗰𝗰𝗶𝗻𝗲 𝗿𝗲𝘀𝘂𝗹𝘁𝘀: 𝗳𝗼𝗹𝗹𝗼𝘄 𝗞𝗲𝘆𝘁𝗿𝘂𝗱𝗮 𝘁𝗼 𝘁𝗵𝗲 𝗱𝗲𝗻𝗱𝗿𝗶𝘁𝗶𝗰 𝗰𝗲𝗹𝗹.
The Phase III INTerpath-001 results circulating today reported a recurrence-free survival hazard ratio of 0.58 for Moderna’s personalized mRNA vaccine plus pembrolizumab versus postoperative pembrolizumab alone. [1]
The comparator matters.
SWOG S1801 had already demonstrated improved outcomes in resectable stage III–IV melanoma by moving three pembrolizumab doses before surgery, while keeping the same planned total number of doses. No manufactured vaccine was added. Treatment timing changed. [2]
Moderna’s trial did not compare its vaccine regimen against that neoadjuvant strategy. For patients eligible for preoperative immunotherapy, its additional benefit over that approach remains untested.
𝗧𝗵𝗲 𝗴𝗹𝗶𝗼𝗯𝗹𝗮𝘀𝘁𝗼𝗺𝗮 𝗿𝗲𝘀𝗲𝗮𝗿𝗰𝗵 𝗿𝗲𝘃𝗲𝗮𝗹𝘀 𝘄𝗵𝘆 𝘁𝗵𝗲 𝗱𝗶𝘀𝗰𝘂𝘀𝘀𝗶𝗼𝗻 𝗺𝘂𝘀𝘁 𝗴𝗼 𝗯𝗲𝘆𝗼𝗻𝗱 𝘁𝗶𝗺𝗶𝗻𝗴.
The initial recurrent-glioblastoma study reported median survival of 13.7 months with preoperative pembrolizumab versus 7.5 months with postoperative treatment. A subsequent neoadjuvant expansion cohort reported 6.8 months and did not confirm the initial survival advantage. [3]
Earlier checkpoint blockade alone had not reliably reproduced the benefit.
UCLA’s combination study investigated pembrolizumab alongside ATL-DC, its personalized tumor-lysate dendritic-cell vaccine, and poly-ICLC immune stimulation.
In the IDH-wildtype subgroup reported at EANO 2026, patients receiving pembrolizumab before surgery and alongside vaccination had median overall survival of 271 days, approximately 8.9 months.
Patients completing vaccination before pembrolizumab had median overall survival of 555 days, approximately 18.2 months. [4]
𝗠𝗼𝗿𝗲 𝘁𝗵𝗮𝗻 𝗱𝗼𝘂𝗯𝗹𝗲 𝘁𝗵𝗲 𝗿𝗲𝗽𝗼𝗿𝘁𝗲𝗱 𝗺𝗲𝗱𝗶𝗮𝗻 𝘀𝘂𝗿𝘃𝗶𝘃𝗮𝗹. 𝗜𝗻 𝗿𝗲𝗰𝘂𝗿𝗿𝗲𝗻𝘁 𝗴𝗹𝗶𝗼𝗯𝗹𝗮𝘀𝘁𝗼𝗺𝗮.
The groups contained 19 and 16 patients, respectively. The reported hazard ratio was 0.32, with p<0.0006. These conference findings came from an amended trial; both groups received dendritic-cell vaccination and checkpoint blockade. [4]
Northwest is also a co-proprietor of granted European patent EP3065772B1, whose claim 6 specifies glioma-lysate dendritic-cell vaccination before a PD-1 inhibitor. [11]
𝗧𝗵𝗲 𝘀𝗲𝗾𝘂𝗲𝗻𝗰𝗲 𝗶𝘀 𝘁𝗵𝗲 𝗰𝗹𝗶𝗻𝗶𝗰𝗮𝗹 𝗼𝗯𝘀𝗲𝗿𝘃𝗮𝘁𝗶𝗼𝗻. 𝗧𝗵𝗲 𝗰𝗲𝗹𝗹𝘂𝗹𝗮𝗿 𝗽𝗮𝗿𝘁𝗻𝗲𝗿𝘀𝗵𝗶𝗽 𝗽𝗿𝗼𝘃𝗶𝗱𝗲𝘀 𝘁𝗵𝗲 𝗺𝗲𝗰𝗵𝗮𝗻𝗶𝘀𝘁𝗶𝗰 𝗿𝗮𝘁𝗶𝗼𝗻𝗮𝗹𝗲.
An Immunity paper states it directly:
“Successful anti-PD-1 cancer immunotherapy requires T cell-dendritic cell crosstalk involving the cytokines IFN-γ and IL-12.”
Garris and colleagues showed that removing dendritic cells, neutralizing IL-12, or disrupting dendritic-cell sensing of interferon gamma prevented effective anti-PD-1 tumor control in their mouse experiments. The drug remained present. Its required cellular partnership had been disrupted. [5]
Activated T cells release interferon gamma. Responsive dendritic cells produce IL-12. IL-12 reinforces the responding T cells.
𝗧𝗵𝗶𝘀 𝗶𝘀 𝗿𝗲𝗰𝗶𝗽𝗿𝗼𝗰𝗮𝗹 𝗹𝗶𝗰𝗲𝗻𝘀𝗶𝗻𝗴.
The instructor supports the effector, and the effector signals back to sustain the instructor. The conversation continues inside the tumor, beyond initial priming.
In human tumor-derived T cells, adding IL-12 to receptor stimulation increased interferon-gamma production in five of six patients’ samples. In mice, combining checkpoint blockade with dendritic-cell activation produced tumor rejection and protection against subsequent tumor challenge. [5]
The baton is passed through a working feedback loop, with a route to immunological memory.
𝗧𝗵𝗮𝘁 𝗶𝘀 𝘄𝗵𝘆 𝘁𝗵𝗲 𝗱𝗲𝗻𝗱𝗿𝗶𝘁𝗶𝗰 𝗰𝗲𝗹𝗹’𝘀 𝗳𝘂𝗻𝗰𝘁𝗶𝗼𝗻𝗮𝗹 𝘀𝘁𝗮𝘁𝗲 𝗺𝗮𝘁𝘁𝗲𝗿𝘀.
Type-1 polarization concerns the capacity to coordinate antigen presentation, costimulation and bioactive IL-12p70 production following appropriate activation.
The target identifies what to recognize. Costimulation supports activation. Cytokine instruction helps determine the response that follows.
Kalinski and Mailliard’s αDC1 research deliberately engineered mature antigen-presenting cells that respond to lymph-node homing signals while retaining IL-12p70-producing capacity. [6]
Carreno’s research tested the distinction directly. Investigators retained the peptide target while changing dendritic-cell activation. In laboratory experiments, the revised signals restored deficient IL-12p70 production and improved antigen-specific T-cell expansion. [7]
𝗦𝗮𝗺𝗲 𝘁𝗮𝗿𝗴𝗲𝘁. 𝗖𝗵𝗮𝗻𝗴𝗲𝗱 𝗶𝗻𝘀𝘁𝗿𝘂𝗰𝘁𝗶𝗼𝗻. 𝗜𝗺𝗽𝗿𝗼𝘃𝗲𝗱 𝗳𝘂𝗻𝗰𝘁𝗶𝗼𝗻.
Moderna’s vaccine supplies instructions for making selected tumor antigens. Its benefit depends on the patient’s antigen-presenting machinery converting that information into effective immunity.
Its protocol started pembrolizumab at randomization and added the vaccine when available. INTerpath-001 did not compare vaccine-first priming with checkpoint-first treatment. [1]
UCLA’s results make that a concrete research question. Garris explains why the functional partnership deserves at least as much attention as the schedule.
𝗧𝗵𝗶𝘀 𝗶𝘀 𝘁𝗵𝗲 𝗯𝗶𝗼𝗹𝗼𝗴𝗶𝗰𝗮𝗹 𝗰𝗮𝘀𝗲 𝗳𝗼𝗿 𝗗𝗖𝗩𝗮𝘅-𝗰𝗲𝗻𝘁𝗲𝗿𝗲𝗱 𝗰𝗼𝗺𝗯𝗶𝗻𝗮𝘁𝗶𝗼𝗻 𝗱𝗲𝘃𝗲𝗹𝗼𝗽𝗺𝗲𝗻𝘁.
DCVax-L is Northwest’s commercially developed treatment within UCLA’s tumor-lysate dendritic-cell research lineage. It supplies personalized tumor material loaded into prepared antigen-presenting cells. [8]
Northwest’s exclusive Kalinski licenses bring specific DC applications and upgrades into its portfolio, including technologies intended to enhance DC function and condition the tumor environment. The maturation research identifies the functional properties to preserve: effective antigen presentation coupled to appropriate type-1 instruction. [6,9]
Eden addresses delivery at scale. Northwest reported that its automated Flaskworks development process produced DCVax-L with substantially comparable biological characteristics, cell function and dose yield to its manual process. The system is intended to expand manufacturing capacity while preserving the properties of the living-cell product. [10]
The process can become more standardized while the tumor material remains patient-specific.
𝗧𝗼𝗱𝗮𝘆’𝘀 𝗺𝗥𝗡𝗔 𝗻𝗲𝘄𝘀 𝘀𝗵𝗼𝘂𝗹𝗱 𝗯𝗿𝗼𝗮𝗱𝗲𝗻 𝘁𝗵𝗲 𝗱𝗲𝗯𝗮𝘁𝗲 𝗯𝗲𝘆𝗼𝗻𝗱 𝘄𝗵𝗶𝗰𝗵 𝗮𝗻𝘁𝗶𝗴𝗲𝗻𝘀 𝗮 𝘃𝗮𝗰𝗰𝗶𝗻𝗲 𝗲𝗻𝗰𝗼𝗱𝗲𝘀.
A personalized vaccine must help establish, direct and sustain the cellular response that checkpoint blockade needs.
DCVax-L makes the antigen-presenting cell part of the treatment. The case for developing combinations around that foundation is supported by the mechanism, the clinical sequencing signal and a manufacturing strategy designed to preserve living-cell function at scale.
𝗧𝗵𝗲 𝗽𝗮𝗽𝗲𝗿 𝗲𝘅𝗽𝗹𝗮𝗶𝗻𝘀 𝘁𝗵𝗲 𝗯𝗶𝗼𝗹𝗼𝗴𝘆. 𝗡𝗼𝘄 𝗮𝘀𝗸: 𝘄𝗵𝗼 𝗵𝗼𝗹𝗱𝘀 𝘁𝗵𝗲 𝗽𝗮𝘁𝗲𝗻𝘁 𝗿𝗶𝗴𝗵𝘁𝘀 𝘁𝗼 𝘁𝗵𝗲 𝘁𝗿𝗲𝗮𝘁𝗺𝗲𝗻𝘁 𝘀𝗲𝗾𝘂𝗲𝗻𝗰𝗲 𝗯𝘂𝗶𝗹𝘁 𝗮𝗿𝗼𝘂𝗻𝗱 𝗶𝘁?
“Successful anti-PD-1 cancer immunotherapy requires T cell-dendritic cell crosstalk involving the cytokines IFN-γ and IL-12.”
Sources:
[1] Moderna, INTerpath-001:
cslide.ctimeetingtech.com/es…
[2] SWOG S1801:
swog.org/news-events/news/20…
[3] Pembrolizumab GBM expansion:
nature.com/articles/s41467-0…
[4] UCLA, EANO 2026:
conpass.floq.live/kiosk/eano…
[5] Garris, reciprocal licensing:
pmc.ncbi.nlm.nih.gov/article…
[6] Type-1-polarized dendritic cells:
pubmed.ncbi.nlm.nih.gov/1534…
[7] Dendritic-cell functional rescue:
jci.org/articles/view/68395
[8] DCVax-L:
doi.org/10.1001/jamaoncol.20…
[9] Northwest’s Kalinski licenses:
nwbio.com/northwest-biothera…
[10] Flaskworks manufacturing:
nwbio.com/northwest-biothera…
[11] Granted combination patent, claims 1 and 6:
patents.google.com/patent/EP…


Breaking: Moderna shares plunged 25% after details of its breakthrough mRNA-based cancer vaccine were shared on social media on.wsj.com/4ic0d0i


Andy Blidy retweeted

If it's not a big enough tragedy to have brain cancer, our healthcare system adds insult to injury where one might have to leave the country to get proper medical treatments. #DCVax $NWBO

Hoping we don’t need these to get treatment for my husbands brain cancer but grateful they came today just incase. @realDonaldTrump @SecKennedy @NorthwestBio @HollensbeAmanda @DrOz @greta

Andy Blidy retweeted

Looking for sustainable protein options? Discover which meats are eco-friendly and how to make greener choices for your health and the planet. #SustainableEating #Nutrition
drweil.com/diet-nutrition/nu…

Andy Blidy retweeted

Amanda, I’m so glad you got that moment. You, Braelyn and Ben made those seconds count. ❤️
I’m sure @POTUS @realDonaldTrump sees the opportunity: a real DCVax cancer moonshot, making the pursuit of cancer cures a defining part of his agenda.
@DrOzCMS @SecKennedy @WhiteHouse @FDA, please grant DCVax-L a National Priority Voucher, extend the Plausible Mechanism Pathway to include it, and open compassionate access here in the United States.
Let’s bring Braelyn’s treatment home.
#DCVaxForBraelyn #DCVax
🙏🏻🙏🏻🙏🏻
Andy Blidy retweeted
$NWBO #DCVax
𝐇𝐞 𝐛𝐮𝐢𝐥𝐭 𝐚 𝐩𝐥𝐚𝐠𝐮𝐞 𝐯𝐚𝐜𝐜𝐢𝐧𝐞 𝐭𝐡𝐚𝐭 𝐰𝐨𝐫𝐤𝐬. 𝐈𝐭 𝐡𝐚𝐬 𝐛𝐞𝐞𝐧 𝐨𝐧 𝐚 𝐬𝐡𝐞𝐥𝐟 𝐬𝐢𝐧𝐜𝐞 𝟐𝟎𝟏𝟐.
On September 25 a 28-year-old technician at the Irkutsk Anti-Plague Research Institute broke a test tube. She was hospitalized with severe pneumonia four days later and died. Two hundred contacts went under observation and all tested negative. Russia has not confirmed plague. Every specialist on the record says the same three things: one laboratory accident rather than an outbreak, treatable with prompt antibiotics, and the real problem is Russian opacity.
Take them at their word. The point is smaller and harder to dismiss.
An institute exists whose entire reason for existing is that organism. People work there. They handle it. And the vaccine the world stocks for exactly those people, F1-V, raises no T cell response anyone has been able to measure.
There is a better one.
Ralph Steinman found the dendritic cell in 1973 and spent 38 years proving it is the cell that decides whether the immune system attacks or stands down. His Nobel was announced three days after he died.
In 2001 his lab mailed a protein to DEC-205, a receptor that sits on dendritic cells and almost nowhere else. Delivery worked beautifully. The T cells divided, never produced interferon gamma, and within seven days were deleted and permanently unresponsive to that antigen. He had built the most efficient device anyone had yet made for teaching a body to ignore something.
In the same paper, the fix. Co-inject an antibody against CD40 and the outcome inverts to immunity. Cella had shown five years earlier that CD40 ligation is specifically what makes a dendritic cell produce IL-12. The address was never the hard part. The alarm was.
Then, dying of pancreatic cancer, he spent his last four years on the other half. Three papers, 2008, 2010 and 2012. LcrV welded into an anti-DEC-205 antibody. Interferon gamma T cells in three separate mouse strains, where F1-V produced none that anyone could find. Protection against CO92, the reference pneumonic strain, which exists because it was taken out of a man who caught it from a cat. Then up the nose: T cells in the airway itself, IgA in the lung, and survival against aerosolized challenge.
The work stopped in 2012 because he was dead. Nobody refuted it. Nobody failed to repeat it.
The part almost nobody knows. While he was running that program he was receiving dendritic cell vaccines built from his own cells, loaded with RNA from his own tumor. Not the elegant addressed version he had spent a decade arguing for. The manufactured kind. He got four and a half years against a six-month prognosis.
He refused to call it evidence, because the sample size was one.
That platform takes any payload. A bacterium, a virus, a tumor. Change the cargo and you have changed the disease, and nothing else about it moves.
In August 2025 HHS cancelled 22 mRNA vaccine programs. In August 2026 an mRNA cancer vaccine cleared a phase 3. Nobody is funding the one that already protected animals against aerosolized plague.
Two hundred people in Siberia spent last week waiting on a test result.
Three papers sit where he left them.
@WHO @CDCgov
X Article: xitter.cf/andrewcaravello/status…

A Russian lab worker has died and thousands are in quarantine after a plague outbreak.
The World Health Organisation says the pneumonic form of plague is especially contagious and "can trigger severe epidemics".
@SkyNewsThomas explains everything you need to know about varieties of the disease.
🔗 trib.al/6kuLirx
Andy Blidy retweeted

So after a 3rd CHM expert panel to advise MHRA on DCVax-L approval, we have NHS announcing they are subsidizing $NWBO manufacturing & supply chain.
UK taxpayer dollars are not underwriting a rejected therapy.
It's clear where this is going my friends.

The UK NHS explicitly stated they are building nationwide logistics for $NWBO DCVax-L to support GBM "as well as all solid tumours."
We do not yet know the exact regulatory sequence to a broad solid tumor label.
Yet the UK single-payer system is making one thing clear: they are planning for full platform scale and they are building the physical infrastructure to support it right now.

Andy Blidy retweeted

$NWBO
@WhiteHouse
@SecKennedy
@SecScottBessent
Great work Braelyn, Mom and Dad!!
Repost everyone knows someone with cancer.
@greta

Please join the NWBO/DCVax/Fight cancer/Hollensbe family !! PLEASE! help them with their financial burden by donating to their GoFundMe @gofundme
Andy Blidy retweeted

Yes, Sir. That’s included in the packet I provided to POTUS and Senator Graham. I have a lot of follow-up emails to send today.
Andy Blidy retweeted
Amanda, that means so much to me. I’m grateful this journey has made us family, and my work alongside you is far from finished. ❤️
You moved mountains for Braelyn. Yesterday, you brought that same determination straight to the President. I believe that conversation will matter far beyond your own family.
Now we keep pushing to turn that opening into access for the families still waiting. I’m right here with you.
It reminds me of movie Inception: one idea takes root until someone believes in it enough to act. Yesterday, you put that idea before the President: bring Braelyn’s treatment home.
Andy Blidy retweeted
We wouldn’t be here today, with Braelyn regaining her health and our family fighting for change in our healthcare system and government if it weren’t for you, Dr. Andrew and the incredible $NWBO / DCvax community. Forever grateful.
Amanda, I’m so glad you got that moment. You, Braelyn and Ben made those seconds count. ❤️
I’m sure @POTUS @realDonaldTrump sees the opportunity: a real DCVax cancer moonshot, making the pursuit of cancer cures a defining part of his agenda.
@DrOzCMS @SecKennedy @WhiteHouse @FDA, please grant DCVax-L a National Priority Voucher, extend the Plausible Mechanism Pathway to include it, and open compassionate access here in the United States.
Let’s bring Braelyn’s treatment home.
#DCVaxForBraelyn #DCVax
🙏🏻🙏🏻🙏🏻
Andy Blidy retweeted

And just like that… a brave young woman and her rock-star loud and proud mother do more than regulators and officials for the future of Americans, and perhaps the world, to usher in the true era of #NWBO’s life-changing treatment! Tenacity incarnate, thy name is Amanda!

🇺🇸❤️ WE MET PRESIDENT TRUMP TONIGHT! ❤️🇺🇸
What an extraordinary evening for our family!
Tonight, Braelyn, Ben, and I had the incredible opportunity to meet President Trump at the rally in Pendleton, South Carolina!
We had only about 20–30 seconds with him, and I knew I needed to make every second count.
I introduced him to Braelyn and thanked him for telling Dr. Oz about her brain cancer story.
I explained that Braelyn had been diagnosed with glioblastoma, the deadliest type of brain tumor, but that today she is CANCER-FREE after receiving DCVax-L, a personalized cancer vaccine developed right here in America!
Yet we must travel all the way to England for her ongoing treatments because we cannot access it here in the United States.
Then something pretty cool happened!
President Trump turned to one of his staffers and instructed them to get me in touch with Dr. Oz!
I also expressed my hope that we could connect with Secretary Kennedy.
As our brief time together came to an end, I made one final appeal:
“Please help bring this American-made treatment back home to America.”
President Trump was incredibly gracious to our family and very kind to Braelyn. We are so grateful for the opportunity to speak with him!
Earlier in the evening, I was also able to give a member of his staff a detailed packet about Braelyn’s journey, DCVax-L, and the obstacles American patients face in accessing promising investigational treatments.
Now we are praying that the connection with Dr. Oz comes through!
Three years ago, Braelyn was given just months to live. Today, she’s 19, attending college, and her latest MRI shows NO EVIDENCE OF DISEASE RECURRENCE!
Tonight, we had the opportunity to bring her story directly to the President of the United States. ❤️
My prayer is that this opens the door to a much bigger conversation—one that could change the future for countless American cancer patients.
📸 We were not permitted to bring our phones into the private meeting with President Trump, so we couldn’t take our own pictures with him. His staff took an official photograph of us together, which we’re told will be emailed to us. I can’t wait to share it! In the meantime, here are some pictures from our unforgettable evening.
Thank you to EVERYONE who helped make tonight possible and to all of you who continue to share Braelyn’s story. You helped us get this far, and we’re not stopping now! ❤️🙏
@realDonaldTrump @DrOzCMS @WhiteHouse
#DCVaxForBraelyn #DCVax


Andy Blidy retweeted

Braelyn’s courage. Amanda’s determination. A family making every second count.
Amanda says they brought Braelyn’s DCVax-L story directly to President Trump. Thank you @HollensbeAmanda for speaking up for your daughter and other families facing brain cancer. $NWBO

🇺🇸❤️ WE MET PRESIDENT TRUMP TONIGHT! ❤️🇺🇸
What an extraordinary evening for our family!
Tonight, Braelyn, Ben, and I had the incredible opportunity to meet President Trump at the rally in Pendleton, South Carolina!
We had only about 20–30 seconds with him, and I knew I needed to make every second count.
I introduced him to Braelyn and thanked him for telling Dr. Oz about her brain cancer story.
I explained that Braelyn had been diagnosed with glioblastoma, the deadliest type of brain tumor, but that today she is CANCER-FREE after receiving DCVax-L, a personalized cancer vaccine developed right here in America!
Yet we must travel all the way to England for her ongoing treatments because we cannot access it here in the United States.
Then something pretty cool happened!
President Trump turned to one of his staffers and instructed them to get me in touch with Dr. Oz!
I also expressed my hope that we could connect with Secretary Kennedy.
As our brief time together came to an end, I made one final appeal:
“Please help bring this American-made treatment back home to America.”
President Trump was incredibly gracious to our family and very kind to Braelyn. We are so grateful for the opportunity to speak with him!
Earlier in the evening, I was also able to give a member of his staff a detailed packet about Braelyn’s journey, DCVax-L, and the obstacles American patients face in accessing promising investigational treatments.
Now we are praying that the connection with Dr. Oz comes through!
Three years ago, Braelyn was given just months to live. Today, she’s 19, attending college, and her latest MRI shows NO EVIDENCE OF DISEASE RECURRENCE!
Tonight, we had the opportunity to bring her story directly to the President of the United States. ❤️
My prayer is that this opens the door to a much bigger conversation—one that could change the future for countless American cancer patients.
📸 We were not permitted to bring our phones into the private meeting with President Trump, so we couldn’t take our own pictures with him. His staff took an official photograph of us together, which we’re told will be emailed to us. I can’t wait to share it! In the meantime, here are some pictures from our unforgettable evening.
Thank you to EVERYONE who helped make tonight possible and to all of you who continue to share Braelyn’s story. You helped us get this far, and we’re not stopping now! ❤️🙏
@realDonaldTrump @DrOzCMS @WhiteHouse
#DCVaxForBraelyn #DCVax

Andy Blidy retweeted
what is the instructions of the immune system ......A dendritic cell may appear mature under a microscope and still be functionally incompetent. Phenotypic maturity—CD83, CD86, HLA-DR expression—does not guarantee IL-12 production, chemokine secretion, cross-presentation efficiency, or resistance to TGF-β reversion. Manufacturing is mechanism. Eden’s sealed cartridge operates on the feedback mathematics Jackson and Blidy measured in 1990: monocytes differentiate under sub-0.1 dyn/cm² perfusion within the viscoelastic window Liu confirmed in Nature Biomedical Engineering(2024)—APC stiffness 1–11 kPa, stress-relaxation 1–5 seconds. Continuous monitoring of pH, dissolved oxygen, glucose, and lactate terminates the run when IL-2R expression plateaus within the CD25-compatible window. For tolerogenic applications, the same closed system preserves state batch to batch—the AutoDECRA lesson: one lot failed because CD86 drifted above threshold during storage, invisible if measured only at baseline. Tolerance has pass/fail boundaries, and drift is failure. When patients recur, DCVax-L is re-manufactured from the recurrent tumor, capturing evolved dark antigens without computational prediction.
Every indication is an expression of the same five-variable framework. Seven immunogenic: GBM (lysate/αDC1/LN→CNS/CD8+NK+CD4 CTL), pancreatic cancer, breast metastasis prevention, cold solid tumors, myeloma, DCVax-Direct, and DCVax as foundational layer. Nine tolerogenic: T1D, transplantation, GVHD, Parkinson’s, MS, SLE, CV repair, IBD, RDEB. Five hybrid and frontier: checkpoint-induced autoimmunity, chronic HBV, post-transplant cancer, breast metastasis prevention, and longevity. The antigen changes. The maturation cocktail changes. The manufacturing chassis does not.
Eight falsifiable predictions follow from the architecture: (1) Dexamethasone below 2 mg improves tipping-point rates. (2) IL-12p70 above the Carreño threshold predicts response across tumor types. (3) High NK activation ratios predict survival in the Pellegatta framework. (4) DC-first outperforms checkpoint-first across cold tumors. (5) Tolerogenic products maintaining CD86 below threshold under TNF-α challenge show superior durability. (6) Low-dose IL-2 during tolerogenic installation enhances Treg:Tcon without effector activation; IL-7 in the same window undermines tolerance. (7) DCVax as foundational layer improves every combination partner. (8) Supercharged DCs compress inter-patient variance by rescuing low-potency patients into the responder pool.
From the 1976 BCG trial at Roswell Park to the 2026 supercharged DC, every era of Blidy’s career contributed a specific molecule, instrument, or concept to the polarity switch. The field debates which antigens to deliver and which platform to use. The question that determines outcome is different: who is teaching the immune system, and what is the quality of that instruction?
Same cells. Same antigens. Same patient. Opposite outcomes. The switch is the polarity of the dendritic cell. Everything else follows.
The reagents Blidy developed at BDMC—CD25, CD45RO/RA, CD28/CD152, CD80/86, CD40/CD40L, CD3⁻/CD16⁺56⁺, and the complete intracellular cytokine panel—are the molecular vocabulary of this platform. Fifty years of contributions to immunology. One continuum from BCG to αDC1