

Philadelphia, PA
Joined March 2013
- Tweets226
- Following798
- Followers431
- Likes4.8K









Abhi Gami retweeted

#Cardioplegia refresher for intensivists:
Cardioplegia is the temporary, reversible arrest of electromechanical cardiac activity during open-heart surgery, allowing the surgeon to operate on a still, bloodless field while preserving myocardial metabolic function.
* Antegrade cardioplegia: The solution is delivered into the aortic root (above the aortic valve) or directly into the coronary ostia via specialized cannulas. It flows down the left and right coronary arteries, perfusing the myocardial capillary beds, and drains primarily through the coronary sinus into the right atrium.
* Retrograde cardioplegia: A balloon-tipped catheter is placed into the coronary sinus (via the right atrium). The solution flows backward through the cardiac venous system into the coronary capillaries and exits via the coronary ostia into the aortic root, where it is vented.
Many complex cardiac operations combine both techniques using antegrade delivery to achieve rapid initial cardiac arrest, followed by retrograde delivery for continuous or intermittent maintenance, especially beyond critical coronary blockages or during valve repairs.


Abhi Gami retweeted

#CardioNuggets
Acceleration time and Ejection time in prosthetic aortic valve assessment:
🔹 AT = time to peak velocity
🔹 ET = total systolic ejection time
Why AT/ET is useful in prosthetic aortic valves:
-Gradients can be misleading—affected by flow, valve size & design
-AVA by continuity often unreliable (LVOT shadowing/artifacts)
🔹 AT/ET > 0.40 = 🚨 obstruction (SVD, pannus, thrombus, PPM)
#CardioNuggets #MedEd


Abhi Gami retweeted

Our fellows take every opportunity to teach! Give Abhi a marker and any writing surface (including a door apparently!) and he is ready to teach. Today he focused on ToF during CICU rounds. Way to go, Abhi!

Abhi Gami retweeted

Right Atrium Anatomy: Surgical Landmarks and ASD Strategy
👉The crista terminalis separates smooth sinus venarum from pectinate muscle and provides a key right atrial orientation landmark.
👉The triangle of Koch—tendon of Todaro, coronary sinus ostium, and septal tricuspid annulus—localizes the AV node.
👉ASD repair depends on defect type, venous connections, septal rims, and conduction proximity, especially near the membranous septum.


Abhi Gami retweeted

Ebstein anomaly is a rare congenital malformation of the tricuspid valve characterized by apical displacement of the septal and posterior leaflets into the right ventricle.
In a normal heart, the anterior, posterior, and septal tricuspid valve leaflets lie in the same annular plane. In Ebstein anomaly:
◼️The septal and posterior leaflets are displaced toward the apex of the right ventricle.
◼️ The anterior leaflet is usually enlarged and may be redundant or sail-like.
◼️The portion of the right ventricle above the displaced leaflets becomes "atrialized," functioning as part of the right atrium.
◼️ The functional right ventricle is consequently smaller, often leading to tricuspid regurgitation and right-sided volume overload.
Clinical presentation ranges from asymptomatic disease to cyanosis, exertional dyspnea, arrhythmias, and right heart failure. The condition is also strongly associated with accessory pathways, particularly Wolff-Parkinson-White syndrome.
Echocardiography is the diagnostic cornerstone, demonstrating apical displacement of the septal leaflet (typically >8 mm/m² body surface area) and assessing the severity of tricuspid regurgitation and right ventricular function.
Reference: Anderson KR, Zuberbuhler JR, Anderson RH, et al. Morphologic spectrum of Ebstein's anomaly of the heart: A review. Mayo Clin Proc. 1979;54:174-180.

Abhi Gami retweeted
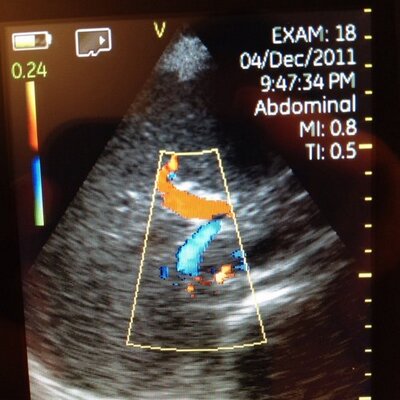
This case illustrates common error in the treatment of drug-induced Torsades.
A patient presents with drug-induced Torsades, most commonly methadone or dofetilide.
They get treated with a bolus of 2-4 grams IV magnesium sulfate and get better.
What happens 4-6 hours later? The magnesium wears off (mostly excreted in the urine). Meanwhile, the methadone or dofetilide is still there (it has a much longer half-life than IV magnesium bolus). So the patient has another episode of Torsades. ☠️
I'm tempted to call this an "error" but it's so commonly done that it's basically the standard of care. So perhaps the term "mishap" is more reasonable.
Repeat episodes of drug-induced Torsades can be prevented using a protocoled magnesium infusion. We started using this about a decade ago. It's safe and easy to do. It makes these cases really boring. The patient sits around on a Mg infusion for 24 hours allowing Mg to soak into their cardiomyocytes while the methadone/dofetilide levels fall. (#1/2)


Abhi Gami retweeted

The @AHAScience Scientific Statement I've been waiting for- Caffeine and Cardiovascular Disease. The science is far from settled, but a comprehensive review of the current evidence is helpful for in-clinic discussions ahajournals.org/doi/10.1161/… @CircAHA ☕️


Abhi Gami retweeted
We are so excited to welcome our newest class of General Cardiology 🫀fellows to the @PennCardiology family! The future of cardiology is bright 🌟
#cardiology #fellowship #penncardiology @MonSangh @noshreza


Abhi Gami retweeted

Rethinking the coronary artery calcium scan: from population averages ... sciencedirect.com/science/ar… @jaideeppatelmd @CiccaroneCenter @hopkinsheart #🥍🐦🫀🏏⚽️⚾️🏀
Abhi Gami retweeted
Hypereosinophilia can cause a variety of different stroke syndromes.
#1 Most common = Watershed infarcts (case below)
1⃣ Not due to hypotension or carotid disease.
1⃣ Mechanism unclear, but might relate to some combination of vascular inflammation & eosinophil-platelet aggregates.
#2 Cardioembolic strokes
2⃣ Due to endocardial thrombi (Loeffler endocarditis).
2⃣ Widely distributed in a typical cardioembolic pattern.
Other stroke patterns are less common:
- Single large territorial infarct
- Lacunar & deep perforator infarcts
- Cerebral venous sinus thrombosis
Take-home messages:
🥡 Eosinophilia >1.5 k/uL is defined as hypereosinophilia. This is unlikely to be due to allergy and requires investigation.
🥡 Always get a CBC *with* differential (otherwise you will miss this). It's more effective to be systematic than smart.
🥡 Eosinophils are angry cells that can wreak havoc on the cerebral vasculature through a variety of mechanisms. Hypereosinophilia of any etiology can cause end-organ damage, including stroke.
(Further discussion: IBCC chapter on eosinophilic lung diseases)


Abhi Gami retweeted
Schematic representation of the main sites of origin of idiopathic premature ventricular contractions and their ECG features.

Abhi Gami retweeted
Rethinking the Coronary Artery Calcium Scan: From Population Averages ... sciencedirect.com/science/ar… Nice editorial by Drs. Vishal Khetpal, @abhigami & @jaideeppatelmd @CiccaroneCenter @hopkinsheart #🥍🐦🫀🏏⚽️🏈🎾
Abhi Gami retweeted

What a fantastic ACC weekend!! Grateful for my cardiology communities! <3 @PennCVFellows @PennCardiology @PaChapterACC @CardioOb @ACCinTouch


So fun to reunite with old friends at #ACC26! Great critical care case presented by @YooJinKimYJK! @OslerResidency @WApplefeld

Abhi Gami retweeted

HOST-EXAM trial 10-year results: Clopidogrel monotherapy is superior to aspirin for chronic maintenance after PCI, significantly reducing both thrombotic and bleeding events. #ACC26 View slides here: clinicaltrialresults.org/wp-…


Abhi Gami retweeted

Also thrilled to share the future leaders of the Osler Resideny—our 2027-2028 ACSs! @maxmcgredy @jackbuyske @mahamkaratela @Liam_P_Coyne @helminthhenry . Our ACSs are the heart of the program & embody our mission and values. We are in great hands with these 5 amazing people!

Abhi Gami retweeted

South Asian adults in the US develop cardiovascular disease risk factors earlier than other groups, according to new research from the MASALA cohort study. Here’s what that means for prevention. ja.ma/3NCyudL
Abhi Gami retweeted

Lots to review but the new dyslipidemia guidelines are out and they recommend at least one-time Lp(a) testing in everyone!
@FamilyHeartFdn @ASPCardio @ACCinTouch @HeartNews @UCSDCardFellows @rblument1
ahajournals.org/doi/10.1161/…

Abhi Gami retweeted

Key updates to this guideline include:
➡️ The use of the American Heart Association PREVENT-ASCVD equations to guide primary-prevention and lipid-lowering therapy decisions.
➡️ Testing Lp(a) at least once in a lifetime and selective apolipoprotein B measurement to improve risk assessment and guide treatment
➡️ The return of LDL-C and non-high-density lipoprotein cholesterol treatment goals (with lower targets for higher-risk groups)
➡️ Expanded use of coronary artery calcium scoring to reclassify risk[ME1.1]
✍🏼 @rblument1 @tygluckman @RonBlankstein @PamelaBMorris @pnatarajanmd @AnnMarieNavar @SethShayMartin @APRN_CNS @nyulangone @DrMichaelShapir @kgradneyrd @eugeniagianos @virani_md @KellieMcLain1 @ijeomaheartdoc @SamiaMoraMD @DrHeatherJohn @dmljmd
